
Care for Life, with Your Own Doctor
From good health to life’s final chapter, a primary care physician who knows you is always by your side.

Why We Need a New Model of Care
- Aging & Chronic IllnessMore people live with several chronic conditions at once, making treatment and medication management increasingly complex.
- Limits of Family CareWith more single-person and elderly households, families can no longer shoulder medical care and caregiving alone.
- Fragmented NavigationPatients visit many hospitals and specialties, yet no one sees the whole picture or connects the pieces.
Medical care and caregiving can no longer be left to individuals and families alone.
Today’s Biggest Problem: Fragmentation
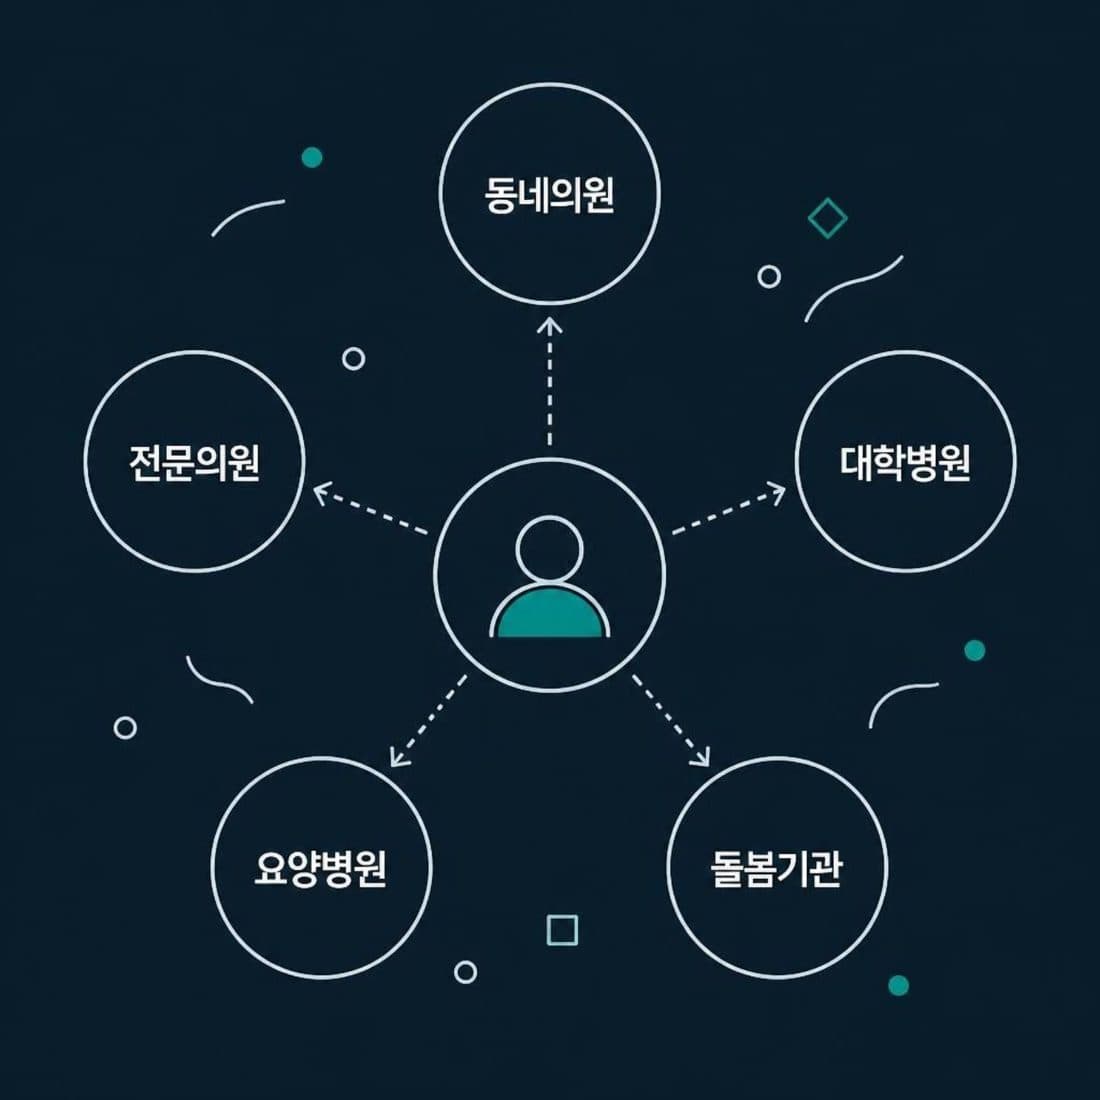
Patients and families shuttle between local clinics, specialist clinics, university hospitals, care hospitals and care agencies, connecting information and carrying every decision themselves.
Who sees the whole picture, connects the dots, and takes responsibility?
- Fragmented treatment
- Risk of duplicate tests
- Growing burden on patients and families
Our Answer: Connection
Not a doctor who treats a single disease, but a primary care physician who knows and cares for a whole life, anchoring every step of care.
- 1Prevention & Wellness
- 2Chronic Care
- 3Specialist Care
- 4Hospital & Surgery
- 5Home Care
From health to the end of life, a doctor who truly knows you is with you.
Not One Doctor Alone, but a Whole Team

Specialist Consultation
Your primary physician consults directly with cardiology, neurology, endocrinology, rehabilitation and mental-health specialists as needed.

Partner Network
Secondary and tertiary hospitals, care hospitals, nurses, pharmacists, social workers and caregivers work as one team.

Continuous Care
Referrals to specialists and hospitals only when truly needed, with your physician knowing you from start to finish.
What the Medical Welfare Social Cooperative Will Do
 1
While You’re Healthy
Prevention, health education, lifestyle coaching and check-up management
 2
When You’re Ill
Lifelong primary care, chronic disease management, specialist collaboration and appropriate care
 3
When Mobility Declines
Home visits by doctors and nurses, home-based medical care and caregiving
 4
To the Very End
Frailty care, palliative care, well-dying and family support
Prevention → Treatment → Home Care → Caregiving & Well-dying: care across the entire life course
Why a Medical Welfare Social Cooperative?
Conventional Providers
The provider delivers services and patients use them when needed. When treatment ends, so does the relationship.
- Service provider
- One-off relationship
- Consumer
Our Co-op
Members invest and participate together, building the healthcare and care system we want.
- Participation
- Trust
- Community
We are not consumers of healthcare; we are owners of a care community.
What Makes Us Different
- 01
Lifelong Primary Physician
Not just a co-op-run clinic, but a doctor who knows you for years and is responsible for your overall health.
- 02
Specialist Advisory Board
You choose one primary physician, yet benefit from the expertise of cardiology, neurology, endocrinology, rehabilitation and more.
- 03
Connected Care
A platform linking primary care → specialists → hospitals → home care → caregiving.
- 04
Appropriate Care
Nothing unnecessary, yet the best medicine and caregiving delivered with dignity.
- 05
Whole-Life Continuum
Health → illness → specialist care → hospitalization → recovery → frailty → home → caregiving → well-dying, seen as one journey.
- No gaps in care: primary, secondary and tertiary care, acute and long-term care hospitals and the home are all connected, plus telemedicine
- Multidisciplinary consultation under the primary physician’s responsibility for remote, appropriate and personalized care
- Medication delivery
- Quality assurance: support for physicians’ academic activities and training, multidisciplinary review
- Hospice care for those who choose to die at home
- Communication and coaching for clinicians, caregivers and service recipients, putting human dignity into practice
- Expanding charitable donations
- Catering
- Coaching education
- Total funeral services
- Cosmetics
- Wellness
One physician who knows you, a team of specialists behind them, and care that continues to the very end.
The Care Team Behind You
Centered on primary care, hospitals, pharmacies, care professionals and educators move as one team.
- Primary care clinic
- Secondary/tertiary & acute care hospitals
- Pharmacies
- Day-care centers
- Home-care nurses
- Care workers
- Social workers
- Coaching & education institutes
- Accounting firm
- 01Internal medicineCardiologyNeurologyEndocrinologyNephrologyGastroenterology
- 02Surgical specialtiesGeneral surgeryNeurosurgeryCardiothoracic surgeryOphthalmologyOtolaryngology (ENT)Obstetrics & gynecologyUrologyOrthopedicsPlastic surgery
- 03Dentistry
Memoranda of understanding (MOUs) with partner institutions will be signed in stages.
A Sustainable Revenue Model
Minimizing Out-of-Pocket Costs
- Participation in prevention programs
- Participation in care-management programs
- Appropriate, personalized care through multidisciplinary teams
※ Treatment beyond what is recommended is fully self-paid.
- Base
Membership Fees
Member capital contributions and joining fees
- Medical
Health Insurance
National Health Insurance reimbursement plus patient co-payments
- Care
Long-Term Care Insurance
Reimbursement for home care and visiting nursing services
- Funding
Donations
Public-interest funding through charitable giving
- Business
Consulting & Coaching Education
Exporting the model and advisory services, coaching education
- Scale-up
Diversification
Expanding into total funeral services, catering, cosmetics and wellness
Total Funeral Services
A funeral is a precious time to mourn the departed and welcome those who come to pay their respects.
The Burden of the Unfamiliar: Funerals
Home is where most Koreans would prefer to spend their final moments, yet only 14% actually die at home.
- Hospice care is hard to access.
- Families are unfamiliar with administrative steps such as death certificates.
- Information on costs, crematoria and burial sites is scarce, and dealing with dominant providers is difficult.
- Families need help sorting the belongings of the deceased.
View as table
| H1 ’18 | 4.77 |
|---|---|
| H2 ’18 | 5.08 |
| H1 ’19 | 5.27 |
| H2 ’19 | 5.58 |
| H1 ’20 | 5.88 |
| H2 ’20 | 6.21 |
| H1 ’21 | 6.66 |
Korea’s Total Funeral Service Landscape
- Large prepaid funeral companies
Funeral hall booking, funeral rites (washing, encoffining, procession, cremation), hearse and burial-site booking
Limitation: Focused on standard packages; little post-death support for single-person households or those without family
- Total funeral specialists
Customized funerals, estate and belongings clean-up, pre-planning (ending notes), services for those without kin
Limitation: No established post-death affairs mandate system like Japan’s
- Estate clean-up companies
Sorting and disposal of belongings, sanitizing and clearing lonely-death sites, estate management
Limitation: Rarely connected directly to funeral services
Most services connect through hospitals and funeral halls; support for deaths at home is almost nonexistent.
Korea vs. Japan
- Service providers
- Korea
- Prepaid funeral firms and a few specialists
- Japan
- Large funeral firms, local funeral directors, NPOs
- Customized funerals
- Korea
- △ Partially offered
- Japan
- ◎ Family, non-religious, natural burials and more
- Estate clean-up
- Korea
- ○ Specialist firms exist
- Japan
- ◎ Integrated with funeral services
- End-of-life planning
- Korea
- △ Early stage
- Japan
- ◎ Advance contracts and ending notes are common
- Support for those without kin
- Korea
- △ Some public support
- Japan
- ◎ Active through NPOs and communities
| Item | Korea | Japan |
|---|---|---|
| Service providers | Prepaid funeral firms and a few specialists | Large funeral firms, local funeral directors, NPOs |
| Customized funerals | △ Partially offered | ◎ Family, non-religious, natural burials and more |
| Estate clean-up | ○ Specialist firms exist | ◎ Integrated with funeral services |
| End-of-life planning | △ Early stage | ◎ Advance contracts and ending notes are common |
| Support for those without kin | △ Some public support | ◎ Active through NPOs and communities |
- ✓Compared with Japan, Korea lacks post-funeral care such as end-of-life planning and estate settlement; services center on the funeral itself.
- ✓Estate clean-up services are growing, and end-of-life planning is developing from an early stage.
Our Total Funeral Services
- 01
Hospice + Bedside Vigil Care
The primary physician and home-care nurse stay with you through the final hours at home.
- 02
Administrative Support
Death certificates, choosing a funeral hall, managing the entire funeral process, memorial video production
- 03
Estate & Post-Death Affairs
Sorting belongings, administrative procedures and digital clean-up services
- Primary physician
- Home-care nurse
- Care worker
- Well-dying caregiver
- Funeral director
- Administrator
How We Will Start and Operate

- 1
Recruit Members
500+ members who share our vision
- 2
Joint Investment
Total capital of KRW 100 million or more
- 3
Open a Primary Care Clinic
A primary care clinic built around lifelong physicians
- 4
Build a Referral Network
Specialist advisory board + partner hospitals
- 5
Prevention to Home Care
Home visits by doctors and nurses, caregiving services
- 6
Expand Locally
Step-by-step growth around neighborhoods
We start small, but build a system that connects an entire life.
Our Roadmap
- STEP 1
Member Recruitment
Citizens, primary care clinicians, home-care nurses, care workers, pharmacists and administrators
- STEP 2
Secondary/Tertiary Hospital MOU
Securing partner hospitals for admission, surgery and specialist care
- STEP 3
Day-Care Center MOU
Building links to daytime care
- STEP 4
Education Partner (IC&RC) MOU
Coaching education for clinicians and caregivers
- STEP 5
Member-Led Prevention Programs
Developing and running participatory health programs
- STEP 6
Total Funeral Services
Launching services that continue to life’s end
Requirements & Founding Process
A medical welfare social cooperative must meet stricter requirements than a standard social cooperative.
- Approving authority
- Social Cooperative
- Relevant ministry
- Medical Welfare Social Cooperative
- Ministry of Health and Welfare
- Minimum members
- Social Cooperative
- 5
- Medical Welfare Social Cooperative
- 500
- Minimum total capital
- Social Cooperative
- No limit
- Medical Welfare Social Cooperative
- KRW 100 million
- Minimum per member
- Social Cooperative
- No limit
- Medical Welfare Social Cooperative
- KRW 50,000
- Maximum per member
- Social Cooperative
- Up to 30% of paid-in capital
- Medical Welfare Social Cooperative
- Up to 10% of paid-in capital
- Use by non-members
- Social Cooperative
- No limit
- Medical Welfare Social Cooperative
- Up to 50% of total supply
| Item | Social Cooperative | Medical Welfare Social Cooperative |
|---|---|---|
| Approving authority | Relevant ministry | Ministry of Health and Welfare |
| Minimum members | 5 | 500 |
| Minimum total capital | No limit | KRW 100 million |
| Minimum per member | No limit | KRW 50,000 |
| Maximum per member | Up to 30% of paid-in capital | Up to 10% of paid-in capital |
| Use by non-members | No limit | Up to 50% of total supply |
Founding Procedure
- 1Recruit Founders
At least five people eligible for membership
- 2Draft Articles
Written by founders and signed by all
- 3Gather Consent
Consent forms submitted to the founders
- 4Announce Assembly
Public notice at least 7 days in advance
- 5Inaugural Assembly
Minutes of the inaugural assembly
- 6Apply for Approval
Filed with the competent ministry
- 7Receive Approval
Issued within 60 days of application
- 8Hand Over Affairs
Founders transfer to the chairperson
- 9Pay in Capital
Members deposit into the chair’s account
- 10Register
At the registry office of the main office
- 11Business Registration
At the tax office of the main office
“Even as I grow old, fall ill, or lose mobility, there is someone who knows me and cares for me.”
A Care Community with Your Lifelong Doctor
- Vision
- As a family-like community, we live lives of dignity and build a healthier society.
- Mission
- We strive for dignified care and medical welfare, put the value of human respect into practice, and build happy lives together.